
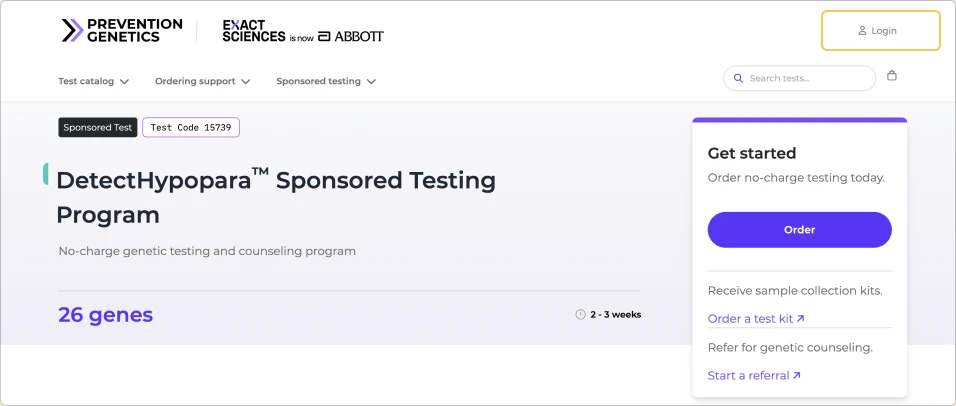
Easy to order, no‑cost genetic tests now available
- Order online; see below
- Kit shipped to your office
- Sample collection choice: blood, saliva, buccal
- Test results sent to your office in approximately 2‑3 weeks after sample receipt
This genetic testing program leverages a whole‑exome backbone using next‑generation sequencing and includes 26 genes known to cause hypoparathyroidism (HypoPT).
The program also partners with DNAvisit to offer no‑cost genetic counseling to support healthcare professionals in helping their patients understand their genetic test results and identifying family members who may also be affected.
Eligibility requirements
Patients are eligible for this program if they reside in the United States or Canada and have 1 of the following diagnoses:

Nonsurgical hypoparathyroidism

Idiopathic hypoparathyroidism

Hypocalcemia suspected to be of genetic cause

Genetic hypoparathyroidism in a relative
The DetectHypopara™ Program
Test Kit Order Form
Sponsored, no‑cost genetic testing (U.S. & Canada)
For repeat orders, we recommend creating an account with PreventionGenetics
Use the secure online portal provided by PreventionGenetics to:
- Submit orders online
- Track progress in real time
- Retrieve reports securely
- Share reports with colleagues
- Manage support requests
Once registered, your dashboard provides a real‑time view of all orders and reports.
Start by creating an account
- Create your account by selecting Login at the top of PreventionGenetics.com and choosing Sign Up on the following page
- Follow the prompts to enter your information and confirm your email address
Note: If you don’t receive a verification or notification email, check your spam folder or ask your IT team to allow emails from [email protected] and [email protected].
Which genes are tested?
26 Gene Panel
The DetectHypopara™ Sponsored Testing Program provides an efficient pathway to sequence a comprehensive panel of 26 genes known to be associated with HypoPT, including both syndromic and familial forms of the condition.
| Disorders of Parathyroid Gland Formation | ||
|---|---|---|
| Gene | Condition(s) | Inheritance |
| ACADM | Medium‑chain acyl‑CoA dehydrogenase deficiency (ACADMD) | AR |
| CHD7 | Coloboma, heart disease, atresia of the choanae, retarded growth and mental development, genital anomalies, and ear malformations and hearing loss (CHARGE) syndrome | AD |
| DHCR7 | Smith‑Lemli‑Opitz syndrome (SLOS) | AR |
| FAM111A | Kenny‑Caffey syndrome type 2 (KCS2), Gracile bone dysplasia (GCLEB) | AD |
| GATA3 | HypoPT, sensorineural deafness, and renal dysplasia (HDR) | AD |
| GCM2 | Familial isolated hypoparathyroidism type 2 (FIH2) | AD, AR |
| HADHA | Mitochondrial trifunctional protein deficiency syndrome (MTPD), long‑chain 3–hydroxyacyl‑CoA dehydrogenase deficiency (LCHAD) | AR |
| HADHB | Mitochondrial trifunctional protein deficiency syndrome (MTPD) | AR |
| NEBL | DiGeorge syndrome type 2 (DGS2) | AD |
| SEMA3E | CHARGE syndrome | AD |
| SOX3 | HypoPT X‑linked recessive (HYPX) | XLR |
| TBCE | HypoPT, retardation, and dysmorphism syndrome (HRDS)/Sanjad‑Sakati syndrome/Kenny‑Caffey syndrome type 1 (KCS1) | AR |
| TBX1 | DiGeorge syndrome type 1 (DGS1) | AD |
| Disorders of PTH Secretion or the PTH Gene | ||
|---|---|---|
| Gene | Condition(s) | Inheritance |
| ATP1A1 | Hypomagnesemia, seizures, and mental retardation (HOMGSMR2) | AD |
| CASR | Autosomal dominant hypocalcemia type 1 (ADH1) | AD |
| CLDN16 | Hypomagnesemia 3, renal (HOMG3) | AR |
| CLDN19 | Hypomagnesemia 5, renal (HOMG5) | AR |
| CNNM2 | Hypomagnesemia 6, renal (HOMG6); hypomagnesemia, seizures, and mental retardation 1 (HOMGSMR1) | AD |
| EGF | Hypomagnesemia 4, renal (HOMG4) | AR |
| FXYD2 | Hypomagnesemia 2, renal (HOMG2) | AD |
| GNA11 | Autosomal dominant hypocalcemia type 2 (ADH2) | AD |
| KCNA1 | Episodic ataxia type 1 (EA1) | AD |
| PTH | Familial isolated hypoparathyroidism type 1 (FIH) | AD, AR |
| SLC12A3 | Gitelman syndrome (GTLMNS) | AR |
| TRPM6 | Hypomagnesemia 1, intestinal (HOMG1) | AR |
| Damage to Parathyroid Glands | ||
| Gene | Condition(s) | Inheritance |
| AIRE | Autoimmune polyendocrinopathy with candidiasis and ectodermal dysplasia (APECED) | AD, AR |
AD=autosomal dominant; AR=autosomal recessive; PTH=parathyroid hormone; XLR=x‑linked recessive.
Clinical Findings
Findings from the DetectHypopara™ genetic testing program1
Over a 2‑year period, 446 individuals who were genetically tested through the DetectHypopara™ Sponsored Testing Program, 50% (n=222) had clinically relevant variants* identified.
*Clinically relevant variants include: pathogenic, likely pathogenic, or variants of unknown significance.
Individuals with identified variants (N=222)
1 in 2
tested had a clinically relevant variant
Calcium-sensing receptor gene (CASR) variants were most common among the 222 affected individuals
Gene variant frequency among 222 affected individuals
†60 individuals had more than one variant identified, reflecting either multiple variants within a single gene or variants identified in multiple genes.
Gain‑of‑function variants in the CASR gene, which encodes the calcium‑sensing receptor (CaSR), are the cause of the disease ADH1 (autosomal dominant hypocalcemia type 1).

ADH1 was the most frequently observed genetic form of HypoPT
—found in 20% of the 446 individuals tests.

Annotated guide to genetic test report
A sample report is provided with highlighted details.
If you need support from a medical geneticist, contact PreventionGenetics Client Services at 715‑387‑0484 or [email protected].
Download reportReference: 1. Mannstadt M, Matthew A, Sridhar A, et al. Genetic Testing of Over 400 Individuals with Non-Surgical Hypoparathyroidism Shows Gain-of-Function CASR Variants As the Most Common Genetic Cause Identified. Poster or Paper presented at: ENDO 2026; June 13-16, 2026; Chicago, IL.